A Lower-Sodium Malaysian Diet: Reducing Salt Without Losing Flavour

Salt is not only the white crystals added at the table. Sodium can also come from soy sauce, oyster sauce, budu, belacan, stock cubes, processed meats, instant noodles, preserved foods and restaurant gravies. This makes reduction difficult when a meal does not taste obviously salty.

The World Health Organization recommends that adults limit salt to less than 5 grams a day, equivalent to less than 2 grams of sodium. Individual medical advice may differ, particularly for kidney, heart or endocrine conditions.

Example of a Malaysian meal where sauces and seasoning affect sodium intake

Key takeaways

  • Reduce salty sauces and seasoning gradually so taste preferences have time to adapt.
  • Use herbs, spices, citrus, garlic, ginger and aromatics to build flavour.
  • Check sodium per serving and the actual number of servings eaten.
  • People with kidney disease or medicines affecting potassium should seek individual advice before using salt substitutes.

Where sodium hides in Malaysian meals

A noodle soup may contain sodium in the broth, seasoning powder, fish balls and sauces added at the table. Nasi campur can become high in sodium when several dishes use gravy, sambal, salted fish or preserved ingredients. Bread, crackers and packaged snacks also contribute across the day.

Rather than labelling one cuisine as unhealthy, look at frequency, portion and preparation. The same dish can vary greatly between home cooking and different restaurants.

CMH dietitian supporting personalised nutrition planning

Practical changes at home

Measure sauces with a teaspoon instead of pouring directly from the bottle. Choose one salty flavouring rather than combining soy sauce, stock powder and table salt. Rinse canned foods when appropriate and compare lower-sodium labels within the same product type.

Add flavour with turmeric, lemongrass, curry leaves, chilli, pepper, lime, onion, garlic and toasted spices. Reduce salt over several weeks; an abrupt change is harder to maintain.

Ordering food outside

Request less sauce or gravy, choose clear portions of vegetables and protein, and avoid drinking all the soup broth. Ask for sauces on the side. Balance a salty meal with less processed choices during the rest of the day instead of skipping meals.

Taste food before adding condiments. A single sachet or spoonful can be more than you need.

Balanced Malaysian food choices for a lower-sodium eating pattern

Read the label correctly

Compare sodium in products using the same serving size or per 100 grams. Check how many servings are in the packet. Claims such as “reduced sodium” do not mean unlimited use.

A dietitian can adapt lower-sodium advice around appetite, culture, budget, blood pressure, kidney function and other nutritional needs.

Getting appropriate care in Seremban

For an individual assessment, contact CMH Dietetics service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.

This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.


References

Getting a Second Medical Opinion: When It Helps and What to Prepare

A second medical opinion is an independent review of a diagnosis, investigation or treatment recommendation. It can provide reassurance, clarify alternatives or reveal that more information is needed. Seeking another view does not automatically mean that the first doctor was wrong.

The most useful second opinions are focused. Decide what question you want answered and provide complete records so the reviewing clinician can assess the same evidence.

Specialist reviewing previous test results for a second medical opinion

Key takeaways

  • Consider another opinion when a diagnosis is uncertain, treatment is major or options carry different trade-offs.
  • Bring original reports, imaging, pathology, medicines and a concise clinical timeline.
  • Ask the second specialist to explain agreements and disagreements clearly.
  • Emergency treatment should not be delayed merely to obtain another routine appointment.

When another opinion may be useful

Patients commonly seek another view before major surgery, long-term treatment or a procedure with significant consequences. It may also help when symptoms continue despite treatment, test findings do not match the clinical picture, or more than one reasonable option exists.

A second opinion is less useful when important records are missing or the question is too broad. Start by writing one or two decisions you need help making.

Doctor and patient comparing medical options during consultation

Build a complete information pack

Prepare clinic letters, discharge summaries, blood results, imaging reports and—where relevant—actual scan images, pathology slides or biopsy reports. Include all current medicines, allergies and previous treatments with dates and outcomes.

Do not selectively remove information because it seems to support one preferred answer. An independent clinician needs the full record to interpret the case responsibly.

How to compare two recommendations

Ask each clinician to explain the working diagnosis, evidence, uncertainty, expected benefit, risks and alternatives. Differences may reflect incomplete data, different clinical experience or more than one acceptable approach.

If opinions differ, ask what additional test or follow-up finding would change the decision. A multidisciplinary discussion may be appropriate for complex conditions.

Hospital where a patient may seek another specialist assessment

Do not delay urgent care

Another opinion should not postpone treatment when delay could cause harm. New severe pain, breathing difficulty, sudden weakness, major bleeding or rapid deterioration needs urgent assessment. Tell the second-opinion clinic if there is a time-sensitive recommendation.

Getting appropriate care in Seremban

For an individual assessment, contact CMH Specialist Hospital in Seremban. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.

This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.

References

Hospital Consent Forms: Questions to Ask Before a Procedure

Signing a consent form should not be the first time a patient hears the important details of a procedure. Consent is a conversation and decision-making process. The form documents that discussion; it does not replace an explanation that the patient can understand.

Patients can ask questions, request clarification and take reasonable time to consider options unless an emergency makes delay unsafe. Malaysian Medical Council guidance emphasises that valid consent requires capacity, adequate information and a voluntary decision.

Doctor explaining a proposed procedure and answering patient questions

Key takeaways

  • Understand the purpose, expected benefit, important risks and reasonable alternatives.
  • Tell the team about medicines, allergies, pregnancy possibility and previous reactions.
  • Ask who will perform the procedure and what recovery or follow-up involves.
  • Do not sign until unclear terms or unexpected changes have been explained.

What informed consent should cover

The discussion should explain what is proposed, why it is recommended and what the likely outcome is. Important risks, limitations and reasonable alternatives—including choosing not to proceed—should be discussed in language suitable for the patient.

The amount of detail depends on the procedure and the individual situation. A person with other illnesses, allergies or special risks may need information that is different from another patient having the same procedure.

Patient participating in an informed healthcare decision

Questions to ask before signing

Ask: What problem is this procedure intended to address? Are there non-procedure options? What are the common and serious risks? What type of anaesthesia or sedation is planned? How long is recovery likely to take? What restrictions will apply afterwards?

Also confirm whether tissue or samples may be taken, when results are expected, and who to contact if symptoms worsen after discharge.

Medicines and fasting instructions

Provide a complete medicines list, especially anticoagulants, antiplatelet medicines, diabetes treatment and supplements. Never stop these products on your own. The procedural team should give individual instructions.

If fasting is required, confirm the start time and whether clear fluids or morning medicines are allowed. Instructions vary according to the procedure and anaesthetic plan.

Hospital setting for a planned medical procedure in Seremban

Can consent be withdrawn?

A patient can raise new questions or change a decision before the procedure. If the planned procedure changes materially, the clinician should explain why and discuss the updated options whenever circumstances allow.

In genuine emergencies, treatment decisions may need to be made quickly. The healthcare team should still communicate as clearly as the situation permits.

Getting appropriate care in Seremban

For an individual assessment, contact CMH Specialist Hospital. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.

This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.

References

Understanding Hospital Referrals: When a Referral Letter May Be Needed

A referral letter is a clinical handover. It tells a specialist why another healthcare professional is requesting an opinion and provides background that may affect assessment or treatment. However, not every private specialist appointment follows exactly the same referral route.

Requirements can depend on the specialty, urgency, insurer, employer panel and hospital policy. Patients should verify the current arrangement directly instead of assuming that a letter is always compulsory—or never needed.

Patient discussing a referral during a hospital consultation

Key takeaways

  • Referral rules vary, particularly when insurance or a corporate panel is involved.
  • A useful letter includes the reason for referral, relevant history, examination findings, tests and current medicines.
  • Urgent symptoms should be directed to emergency care rather than delayed for routine paperwork.
  • Keep copies of referral letters and subsequent specialist reports for continuity.

What information does a referral carry?

A referral commonly explains the main concern, how long it has been present, treatment already tried and why specialist input is requested. It may include relevant medical conditions, allergies, pregnancy status, current medicines, laboratory results and imaging.

This background helps the specialist prepare and decide whether additional records or tests are needed. It also reduces the risk that important previous findings are lost between different parts of the health system.

Doctor reviewing referral information and previous medical reports

Situations where a letter may matter

Some insurers, managed-care organisations and employer panels require referral documentation or a guarantee letter before they authorise specialist care. Certain specialist services may also prefer a referral so that an appropriate appointment type can be arranged.

Self-paying patients may have different access arrangements. Always ask the hospital and your payer what is required before the visit, because administrative rules can change.

Routine referral or emergency care?

Referral appointments are designed for planned assessment. Severe chest pain, sudden weakness on one side, difficulty breathing, major bleeding, loss of consciousness or a suddenly cold and painful limb should not wait for a routine referral. Seek emergency assistance promptly.

For a concerning but stable problem, tell the referring clinic if symptoms worsen while you are waiting. The clinical team can advise whether the urgency needs to change.

Hospital destination for a specialist referral in Seremban

What to do after the specialist visit

Ask how the specialist’s findings will be communicated to the referring clinician. Keep a copy of the clinic letter or report when available. Confirm who will prescribe ongoing medicines, arrange tests and monitor results.

Good referral care is a two-way process: the first clinician provides context, and the specialist returns a focused assessment and plan.

Getting appropriate care in Seremban

For an individual assessment, contact CMH Specialist Hospital. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.

This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.

References

Your First Specialist Appointment: Records, Medicines and Questions to Bring

A first appointment with a specialist is more useful when the doctor can see the full story—not only the symptom that brought you to the clinic. A short preparation checklist can save time, reduce forgotten details and help you leave with a clearer plan.

The exact documents needed vary by specialty, insurer and hospital arrangement. If you are unsure, contact the hospital before travelling. The practical steps below can help patients preparing for a specialist appointment in Seremban.

CMH Specialist Hospital in Seremban for a specialist appointment

Key takeaways

  • Bring identification, appointment details and any referral or guarantee-letter documents you were given.
  • Prepare an accurate medicines list, including supplements and non-prescription products.
  • Organise previous reports and images by date so the specialist can review the sequence.
  • Write down your main symptoms and two or three priority questions.

Start with a one-page health summary

Write the main problem in one sentence, followed by when it started and how it has changed. Include previous diagnoses, operations, allergies and important family history. A timeline is especially helpful when symptoms have come and gone for months.

Note what makes the problem better or worse, whether it affects sleep or daily activity, and any warning symptoms such as fainting, weakness, unexplained weight loss or fever. Do not leave out information because it seems unrelated; the specialist can decide what matters.

Doctor reviewing previous medical records and test results with a patient

Bring a complete medicines list

List each medicine name, strength, dose and how often you take it. Include inhalers, injections, vitamins, traditional preparations and supplements. Photographs of labels can help when you cannot remember a brand or dose.

Do not stop prescribed medicines before the appointment unless a healthcare professional has specifically instructed you to do so. If a test may require fasting or temporary medicine changes, confirm the instructions with the clinic.

Organise previous tests and reports

Bring relevant blood results, scan reports, discharge summaries, procedure notes and clinic letters. If you have imaging on a disc or access through a patient portal, ask whether the specialist can view that format. Arrange records from oldest to newest and mark the most recent result.

Previous information does not always remove the need for new testing, but it may help the specialist understand trends and avoid unnecessary repetition.

Patient discussing health concerns during a specialist consultation

Questions worth asking

Useful questions include: What are the likely causes? Do I need tests now? What are the benefits and limitations of each option? What symptoms should make me seek urgent help? When and how will I receive results? Who should I contact if the problem changes?

Before leaving, repeat the plan in your own words. Confirm the next appointment, medicine changes, test arrangements and the person or department responsible for follow-up.

When another person may help

A trusted family member can help with notes, translation or remembering instructions, especially when the discussion is complex. The patient’s privacy and preferences still come first. Ask the clinic in advance if you need language or mobility support.

Getting appropriate care in Seremban

For an individual assessment, contact CMH Specialist Hospital in Seremban. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.

This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.

References

Menopause and Perimenopause: When to Seek Gynaecology Care in Seremban

Menopause and Perimenopause: When to Seek Gynaecology Care in Seremban

Perimenopause is the transition leading to menopause, when ovarian hormone production fluctuates and periods may become irregular. Menopause is reached after 12 consecutive months without a menstrual period when no other cause explains the change. Symptoms vary widely and can affect sleep, concentration, mood, sexual comfort and daily function.

If symptoms are troublesome or bleeding is unusual, a gynaecologist in Seremban can help assess other possible causes and discuss treatment based on your medical history and preferences.

Key takeaways

What to knowWhy it matters
Perimenopause can begin before periods stopCycle changes, hot flushes and sleep or mood symptoms may occur for months or years before menopause.
Postmenopausal bleeding is not normalAny bleeding after 12 months without a period should be medically assessed.
Treatment is personalisedLifestyle measures, non-hormonal treatments and menopausal hormone therapy have different benefits and risks.
Menopause consultation with a gynaecologist in Seremban
Menopause care should consider symptoms, medical history, personal preferences and long-term health.

Common menopause and perimenopause symptoms

  • Hot flushes and night sweats
  • Irregular, heavier or lighter periods during the transition
  • Difficulty sleeping and daytime fatigue
  • Mood changes, anxiety or reduced concentration
  • Vaginal dryness, discomfort during sex or urinary symptoms
  • Headaches, joint aches or palpitations
  • Changes in sexual desire

Not every midlife symptom is caused by menopause. Thyroid conditions, anaemia, sleep disorders, depression, medicine effects and other illnesses can overlap. Clinical history helps determine whether additional tests are needed.

When should you see a gynaecologist?

Arrange an appointment when symptoms disrupt sleep, work, relationships or emotional wellbeing; when vaginal or urinary symptoms are persistent; or when you want to discuss treatment choices. Earlier review is also appropriate for symptoms before age 45, especially if periods stop early.

Bleeding after sex, very heavy bleeding, prolonged bleeding or any bleeding after menopause needs assessment. Possible evaluation includes examination, cervical screening status review, blood tests, pelvic ultrasound or sampling of the uterine lining depending on age, symptoms and risk.

Gynaecology consultation in Seremban about irregular periods
A menstrual record can help a gynaecologist understand changes in cycle timing and bleeding.

What treatment options are available?

Practical measures include keeping the bedroom cool, regular physical activity, reducing personal hot-flush triggers, sleep routines and pelvic-floor or vaginal moisturiser strategies where appropriate. Cognitive behavioural approaches may help some symptoms.

Menopausal hormone therapy can be effective for hot flushes and certain genitourinary symptoms, but the type and route depend on whether you have a uterus and your medical history. It may not be suitable for everyone. Non-hormonal medicines and local vaginal treatments are alternatives in selected situations. Discuss benefits, risks and follow-up rather than using another person’s regimen.

Long-term health after menopause

Falling oestrogen levels are associated with bone loss, and cardiovascular risk rises with age. Review blood pressure, cholesterol, diabetes risk, smoking, physical activity, nutrition and bone-health risk factors. Screening recommendations should be tailored to age and history.

CMH’s obstetrics and gynaecology service lists menopause care among its clinical services. A consultation can coordinate symptom treatment with broader preventive health needs.

Pelvic ultrasound during a gynaecology assessment in Seremban
Pelvic ultrasound may help assess the uterus and ovaries when clinically appropriate.

When symptoms need urgent care

Seek urgent assessment for very heavy bleeding with fainting or breathlessness, sudden severe pelvic pain, chest pain, stroke-like symptoms or severe mental-health distress. These should not be assumed to be menopause.

How to prepare for your consultation

  • Record period dates, bleeding changes and symptom frequency
  • List previous operations, blood clots, cancers, migraines and liver conditions
  • Bring a complete medicine and supplement list
  • Note family history of breast, ovarian or uterine cancer and osteoporosis
  • Write down your priorities, such as sleep, hot flushes, sexual comfort or bone health

Frequently asked questions

Do I need a hormone test to diagnose menopause?

For many people over 45 with typical symptoms, diagnosis is based mainly on history. Hormone testing may be considered when age, symptoms or medical circumstances make the diagnosis uncertain.

Can pregnancy occur during perimenopause?

Yes. Ovulation can still occur while cycles are irregular. Discuss contraception and when it can be stopped with a healthcare professional.

Is bleeding after menopause ever normal?

It should always be assessed, even if it happens only once or is light spotting. Many causes are benign, but evaluation is important.

Medical references

This article is for general education. A clinician should assess unusual bleeding and advise on individual treatment risks and benefits.

Uterine Fibroids in Seremban: Symptoms, Diagnosis and Treatment Options

Uterine Fibroids in Seremban: Symptoms, Diagnosis and Treatment Options

Uterine fibroids are non-cancerous growths that develop from muscle and connective tissue in or around the uterus. Some are very small and cause no problems. Others can contribute to heavy periods, pelvic pressure, urinary frequency, constipation, pain or fertility concerns. Symptoms—not size alone—help guide management.

A consultation with a gynaecologist in Seremban can clarify whether fibroids are likely to explain your symptoms and which treatment options fit your age, health and pregnancy plans.

Key takeaways

What to knowWhy it matters
Fibroids are usually benignThey are not uterine cancer, and many people need only monitoring.
Location mattersFibroids within the uterine cavity may affect bleeding or fertility differently from those in the muscle wall or outer surface.
Treatment is individualOptions range from observation and medicine to procedures or surgery, depending on symptoms and goals.
Pelvic ultrasound during a gynaecology assessment in Seremban
Pelvic ultrasound may help assess the uterus and ovaries when clinically appropriate.

Possible symptoms of fibroids

  • Heavy or prolonged menstrual bleeding
  • Pelvic pressure, fullness or pain
  • Frequent urination or difficulty emptying the bladder
  • Constipation or pressure on the rectum
  • Abdominal enlargement
  • Pain during sex
  • Anaemia-related fatigue, dizziness or breathlessness
  • Fertility or pregnancy concerns in some cases

These symptoms overlap with adenomyosis, endometriosis, ovarian conditions and other causes of abnormal bleeding or pelvic pain. An examination and appropriate testing help avoid assuming that every symptom is caused by a known fibroid.

How are fibroids diagnosed?

Assessment begins with menstrual and symptom history and may include pelvic examination. Ultrasound is commonly used to assess the uterus, fibroid number, size and location. In selected cases, saline ultrasound, hysteroscopy or MRI may provide more detail. A full blood count can check for anaemia when bleeding is heavy.

If you have older ultrasound reports, bring them. Comparison over time can help distinguish stable fibroids from growth that needs further evaluation.

Gynaecology consultation in Seremban about irregular periods
A menstrual record can help a gynaecologist understand changes in cycle timing and bleeding.

When is treatment needed?

Fibroids without symptoms may only need observation. Treatment is more likely when bleeding causes anaemia, pain or pressure affects daily life, urinary or bowel symptoms are significant, or fibroids may be affecting fertility. The approach should consider how close you are to menopause and whether you wish to preserve the uterus or future pregnancy potential.

Treatment options to discuss

Medicines can reduce bleeding or pain, although they do not suit everyone and may not remove the fibroid. Hormonal treatments, tranexamic acid and anti-inflammatory medicines are among the options a clinician may discuss based on your medical history.

Procedural and surgical options include hysteroscopic removal for selected cavity fibroids, myomectomy, uterine artery embolisation and hysterectomy. Availability and suitability depend on fibroid features, symptoms, fertility goals and other health considerations. Each option has benefits, limitations and recovery implications.

Menopause consultation with a gynaecologist in Seremban
Menopause care should consider symptoms, medical history, personal preferences and long-term health.

When bleeding or pain is urgent

Seek urgent care for very heavy bleeding with fainting, marked dizziness, breathlessness or chest discomfort. Sudden severe pelvic pain, fever, vomiting or pain with possible pregnancy also requires prompt assessment.

Questions to ask at your appointment

  • How many fibroids are present and where are they located?
  • Could another condition be contributing to my symptoms?
  • Do I have anaemia, and should iron be checked?
  • Which options preserve fertility or the uterus?
  • What are the likely benefits, risks and recovery time?
  • What follow-up is needed if I choose observation?

Frequently asked questions

Can fibroids become cancer?

Typical fibroids are benign. A rare cancer called leiomyosarcoma can arise in the uterus, but it is not considered the usual transformation of a fibroid. New or concerning findings need specialist evaluation.

Do fibroids shrink after menopause?

Many shrink as hormone levels fall, but not all symptoms should be attributed to fibroids. New bleeding after menopause always requires assessment.

Can I become pregnant with fibroids?

Many people do. The effect depends on size and location. A fertility-focused assessment is helpful when conception is difficult or a fibroid distorts the uterine cavity.

Medical references

This article is general education. Treatment choice requires an individual examination and review of imaging, symptoms and reproductive goals.

Irregular Periods in Seremban: When to See a Gynaecologist

Irregular Periods in Seremban: When to See a Gynaecologist

A menstrual cycle can vary occasionally, especially during puberty, after pregnancy or while approaching menopause. However, a clear change from your usual pattern, very heavy bleeding, bleeding between periods or long gaps without menstruation can indicate a condition that deserves assessment.

A gynaecologist in Seremban can review cycle history, pregnancy possibility, medicines, hormonal symptoms and other health factors before deciding which tests are appropriate.

Key takeaways

What to knowWhy it matters
Irregular means different from your normal patternUseful details include cycle interval, duration, flow, pain and bleeding between periods or after sex.
Pregnancy should be consideredA missed or unusual period may need a pregnancy test, including when contraception is used.
Heavy bleeding can cause anaemiaFatigue, breathlessness, dizziness or paleness alongside heavy periods should prompt medical review.
Gynaecology consultation in Seremban about irregular periods
A menstrual record can help a gynaecologist understand changes in cycle timing and bleeding.

What counts as an irregular period?

Irregularity may involve periods arriving much earlier or later than expected, cycles that vary widely, bleeding that lasts longer than usual, skipped periods or unexpected spotting. A single variation may follow stress or illness; repeated change is more informative.

Track the first day of each period, bleeding duration, flow, clots, pain and any bleeding between periods. Also record new medicines, weight change, acne, excess facial hair, hot flushes or pregnancy symptoms.

Common reasons cycles change

  • Pregnancy and pregnancy-related conditions
  • Stress, significant weight change or intensive exercise
  • Polycystic ovary syndrome (PCOS)
  • Thyroid or prolactin disorders
  • Hormonal contraception or other medicines
  • Perimenopause
  • Fibroids, polyps, infection or other uterine and cervical conditions

Age and life stage matter. Irregularity soon after periods begin can differ from new bleeding changes in the forties. Bleeding after menopause always requires medical assessment.

Pelvic ultrasound during a gynaecology assessment in Seremban
Pelvic ultrasound may help assess the uterus and ovaries when clinically appropriate.

When should you arrange an appointment?

Book a medical review if irregularity persists, periods stop for several months without an expected reason, bleeding occurs between periods or after sex, or flow becomes significantly heavier or more painful. You should also seek advice if cycle changes occur with difficulty becoming pregnant, symptoms of anaemia or signs of hormonal imbalance.

During assessment, a doctor may ask about pregnancy possibility, contraception, medicines, weight change, stress and family history. Tests can include a pregnancy test, full blood count, thyroid or other hormone tests and cervical assessment. Pelvic ultrasound may be considered when structural causes such as fibroids or ovarian cysts are possible.

When bleeding is urgent

Seek urgent care for very heavy bleeding that soaks through pads or tampons rapidly, especially with dizziness, fainting, breathlessness, chest discomfort, severe abdominal pain or possible pregnancy. Sudden severe pain with bleeding in early pregnancy can be an emergency.

Go to an emergency department or contact local emergency services if symptoms are severe. Do not delay because the bleeding temporarily slows if you feel faint or unwell.

Menopause consultation with a gynaecologist in Seremban
Menopause care should consider symptoms, medical history, personal preferences and long-term health.

Treatment depends on the cause

Management may involve observation, iron treatment, hormonal options, treatment of thyroid or other medical conditions, or procedures for selected structural problems. Fertility plans, age, symptom severity and personal preferences influence the approach. A diagnosis should guide treatment rather than choosing a method from symptoms alone.

The CMH obstetrics and gynaecology service lists care for irregular menstruation, ovarian cysts, fibroids, pelvic pain, menopause and fertility concerns.

Frequently asked questions

Can stress delay a period?

Yes. Stress can affect hormonal signals involved in ovulation. Persistent or marked changes still deserve assessment, especially when pregnancy or another condition is possible.

Does an irregular cycle always mean PCOS?

No. PCOS is one possible cause among many. Diagnosis considers menstrual pattern, androgen-related features and sometimes ultrasound or laboratory findings.

Should I use a period-tracking app?

An app or paper calendar can help identify patterns, but it is not diagnostic. Bring the record to your appointment.

Medical references

This article provides general information and does not replace a pregnancy test or medical assessment.

Early Signs of Kidney Disease: When Should You See a Nephrologist?

Early Signs of Kidney Disease: When Should You See a Nephrologist?

Early chronic kidney disease often has no noticeable symptoms. The kidneys have considerable reserve, so a person may feel well even while filtration is declining or protein is leaking into the urine. Screening people at higher risk is therefore more reliable than waiting for pain or swelling.

A referral to a nephrologist in Seremban may be appropriate when kidney results are persistently abnormal, decline rapidly, the cause is uncertain or complications require specialist management.

Key takeaways

What to knowWhy it matters
No symptoms does not mean no kidney diseaseBlood and urine tests can detect problems before advanced symptoms appear.
Diabetes and hypertension are major risksControlling blood glucose and blood pressure helps protect kidney and cardiovascular health.
Referral urgency depends on the patternRapidly worsening function, severe electrolyte disturbance or major protein or blood in urine may need faster assessment.
Nephrology consultation in Seremban reviewing kidney function results
Kidney results are interpreted together with medical history, medicines and previous readings.

Who is at higher risk?

  • People with diabetes or long-standing high blood pressure
  • Those with heart disease, vascular disease or previous stroke
  • People with a family history of kidney failure
  • Anyone with autoimmune disease, recurrent stones or urinary obstruction
  • People with past acute kidney injury
  • Those taking medicines that may affect kidney function, especially during dehydration or illness

Risk does not mean disease is inevitable. It means periodic blood pressure, eGFR and urine albumin checks may be valuable. Ask your doctor how often testing is appropriate for your health history.

Possible signs as kidney disease progresses

Later kidney disease can cause ankle or facial swelling, foamy urine, blood in urine, reduced or increased urination, persistent itching, poor appetite, nausea, muscle cramps, fatigue, sleep difficulty or shortness of breath. These symptoms are not specific and can occur with many other conditions.

Kidney pain is not a usual feature of chronic kidney disease. Pain in the side or back may instead relate to stones, infection or another cause and should be assessed according to severity and accompanying symptoms.

Blood and urine samples for kidney function testing in Seremban
Blood creatinine, eGFR and urine albumin tests provide different information about kidney health.

Which results can prompt nephrology review?

Doctors consider the eGFR level, rate of change, urine albumin or protein, blood or abnormal cells in urine, blood pressure and electrolyte results. Referral may also be helpful when kidney disease appears hereditary, a systemic or inflammatory condition is suspected, or treatment-resistant hypertension may have a kidney-related cause.

A nephrologist reviews the entire pattern rather than one threshold in isolation. Previous laboratory reports are especially useful because they show whether a change is new, stable or progressive.

What happens at a nephrology appointment?

The consultation may cover diabetes and blood-pressure control, medicines, supplements, fluid balance, family history and urinary symptoms. Examination often includes blood pressure and signs of fluid retention. Repeat blood or urine tests, ultrasound or selected immune and genetic tests may be considered.

Treatment focuses on the underlying cause, slowing progression and managing complications. This can include blood-pressure and diabetes care, medicine review, dietary advice and monitoring. CMH’s nephrology service also covers glomerular disease evaluation, kidney biopsy and dialysis care where clinically required.

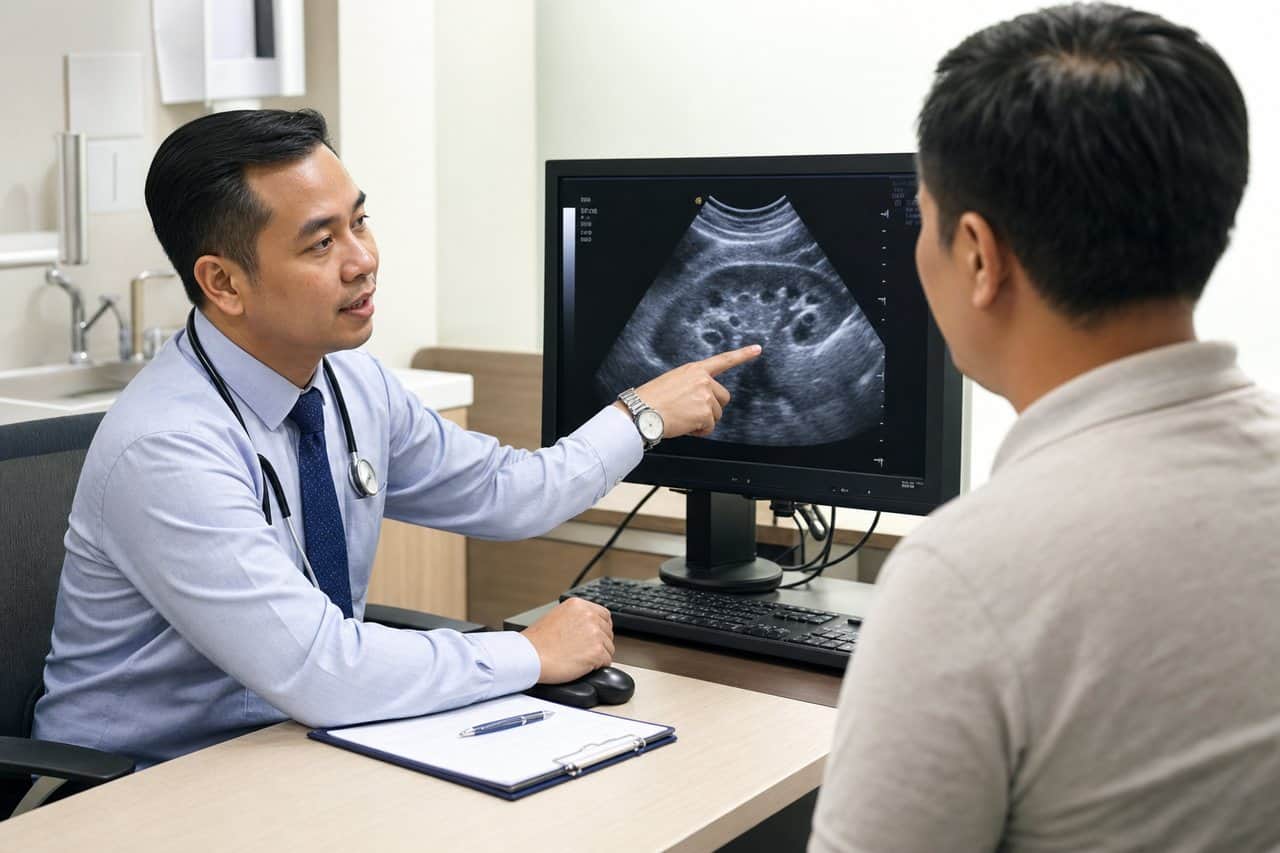
Doctor explaining a kidney ultrasound during a nephrology assessment in Seremban
Imaging may be considered when a doctor needs to assess kidney structure or urinary obstruction.

When kidney symptoms are urgent

Seek urgent medical care for very little or no urine, rapidly worsening swelling, severe breathlessness, confusion, chest pain, persistent vomiting, fainting or profound weakness. Fever with severe flank pain or urinary symptoms can indicate kidney infection and also requires prompt assessment.

How to protect kidney health

  • Keep diabetes and blood pressure under regular medical review
  • Take prescribed medicines consistently and discuss side effects
  • Avoid frequent unsupervised use of painkillers that can affect kidneys
  • Stay appropriately hydrated, particularly during illness, unless on fluid restriction
  • Avoid unregulated supplements or remedies with uncertain ingredients
  • Stop smoking and manage cardiovascular risk factors

Frequently asked questions

Can kidney disease be reversed?

Some acute causes improve when treated promptly. Chronic scarring may not reverse, but progression can often be slowed by treating the cause and controlling risk factors.

Will I need dialysis if I see a nephrologist?

No. Much of nephrology care involves diagnosis, monitoring and protecting remaining kidney function. Dialysis is considered only when kidney failure and its complications reach a stage where replacement therapy is needed.

What should I bring?

Bring recent and older laboratory reports, imaging, a full medicine and supplement list, home blood-pressure readings and relevant hospital records.

Medical references

This article is educational and does not replace an individual kidney assessment.

Kidney Function Tests in Seremban: Creatinine, eGFR and Urine Protein Explained

Kidney Function Tests in Seremban: Creatinine, eGFR and Urine Protein Explained

Kidney function is not assessed by one number alone. A blood creatinine result is used to estimate the glomerular filtration rate (eGFR), while a urine albumin test looks for protein leakage. Together with blood pressure, medical history and previous results, these tests help identify kidney damage and track change over time.

People with diabetes, high blood pressure, heart disease or a family history of kidney failure may need regular checks. When results are persistently abnormal or decline, a nephrologist in Seremban can interpret the pattern and advise on further assessment.

Key takeaways

What to knowWhy it matters
Creatinine and eGFR are linkedCreatinine is measured in blood; eGFR estimates filtration after accounting for factors such as age and sex.
Urine albumin adds different informationProtein leakage can signal kidney damage even when eGFR is still relatively preserved.
Trends are often more useful than one resultTemporary illness, dehydration, medicines and laboratory variation can affect readings, so confirmation may be needed.
Blood and urine samples for kidney function testing in Seremban
Blood creatinine, eGFR and urine albumin tests provide different information about kidney health.

What is creatinine?

Creatinine is a waste product generated by normal muscle activity. Healthy kidneys remove it from the blood. When kidney filtration falls, blood creatinine commonly rises. However, creatinine is also influenced by muscle mass, diet, age and some medicines, so the same value can mean different things for different people.

A clinician interprets creatinine with eGFR, previous results and your overall condition. A small change may be important when it occurs quickly, while a stable value may need monitoring rather than immediate intervention.

What does eGFR mean?

Estimated glomerular filtration rate expresses kidney filtration as an estimate, usually reported in mL/min/1.73 m². Lower values generally indicate reduced filtration. Chronic kidney disease is defined by kidney damage or reduced function that persists over time; one isolated result does not always establish chronic disease.

If eGFR drops suddenly, doctors consider acute kidney injury, dehydration, infection, urinary obstruction, medicine effects and other causes. Rapid change may require prompt assessment.

Nephrology consultation in Seremban reviewing kidney function results
Kidney results are interpreted together with medical history, medicines and previous readings.

Why test urine albumin or protein?

Kidney filters normally keep most protein in the bloodstream. Albumin in urine can therefore be an early sign of filter damage. A urine albumin-to-creatinine ratio (UACR or ACR) adjusts for urine concentration and is commonly used for screening and monitoring.

Exercise, fever, urinary infection, menstruation and very high blood pressure can temporarily increase urine protein. An abnormal result may be repeated under suitable conditions. Visible blood in urine, persistent protein or other abnormalities need medical evaluation.

Who may need kidney testing?

  • People with diabetes or high blood pressure
  • Those with heart or blood-vessel disease
  • People taking medicines that can affect kidney function
  • Anyone with a family history of kidney failure or inherited kidney disease
  • People with recurrent kidney stones, urinary obstruction or autoimmune disease
  • Anyone with swelling, foamy urine, blood in urine or an unexplained fall in urine output

What other tests may be considered?

Depending on the situation, assessment can include electrolytes, full blood count, blood glucose, autoimmune tests, urine microscopy or imaging. Kidney ultrasound can assess size, structure and possible obstruction. A kidney biopsy is reserved for selected cases where tissue diagnosis may change treatment.

CMH’s medical laboratory supports diagnostic testing, while the nephrology service describes evaluation and management of kidney conditions.

Doctor explaining a kidney ultrasound during a nephrology assessment in Seremban
Imaging may be considered when a doctor needs to assess kidney structure or urinary obstruction.

When to seek urgent care

Seek urgent assessment for a major reduction in urine output, severe breathlessness, confusion, persistent vomiting, rapidly increasing swelling, severe weakness, chest pain or sudden worsening in a person with known kidney disease. These symptoms can reflect fluid, electrolyte or kidney-function problems that should not wait for a routine appointment.

Frequently asked questions

Can dehydration change creatinine?

Yes. Reduced fluid intake, vomiting or diarrhoea can affect kidney perfusion and raise creatinine. The context and degree of change determine the response.

Does a low eGFR always mean dialysis?

No. eGFR covers a wide range of kidney function. Many people with chronic kidney disease are managed with risk-factor control and monitoring. Dialysis decisions depend on overall function, symptoms and complications—not one result alone.

Should I repeat an abnormal test?

Often, but timing depends on severity and whether acute illness is present. Follow the clinician’s advice rather than delaying a clearly urgent result.

Medical references

This article is general information. Laboratory reference ranges and clinical decisions vary with the individual and testing context.