

Compare shared and sex-specific health-screening tests, understand tumour-marker limits and choose a personalised package in Seremban.
Post-Thrombotic Syndrome: Persistent Leg Swelling After a Blood Clot
Some people continue to have leg swelling, aching, heaviness or skin changes after a deep vein thrombosis (DVT). This long-term complication is called post-thrombotic syndrome. It develops when the clot and inflammation damage veins or their valves, making it harder for blood to return from the leg.
New or suddenly worsening symptoms still need assessment because a recurrent DVT can feel similar. A previous clot should never be used to dismiss a new change.

Key takeaways
- Post-thrombotic syndrome can cause chronic swelling, heaviness, discomfort and skin discolouration.
- Sudden worsening requires assessment for another clot or another cause.
- Compression is not suitable for everyone and should be individually assessed.
- Protecting the skin and maintaining suitable movement can support long-term care.
Why symptoms remain after DVT
A DVT blocks a deep vein and can injure one-way valves that normally help blood travel back to the heart. Even after anticoagulant treatment, residual obstruction or valve damage may leave higher pressure in the lower-leg veins.
Symptoms often worsen after long periods of standing or sitting. They may improve with walking or leg elevation, but patterns vary.

Symptoms to discuss with a clinician
Common features include swelling, aching, heaviness, cramps, itching, tingling, visible veins and darker skin near the ankle. Severe disease can cause eczema-like inflammation or a venous ulcer.
The clinician may compare both legs, examine the skin and pulses, review the original DVT and arrange ultrasound when a new clot or persistent obstruction is suspected.
Management is individual
A plan may include suitable walking and calf-muscle activity, weight management, periods of elevation, moisturising dry skin and properly fitted compression. Compression strength and suitability should be assessed, especially when arterial circulation may also be reduced.
Continue anticoagulants exactly as prescribed. They prevent clot extension and recurrence but do not instantly repair damaged valves. Never change treatment without medical advice.
Red flags after a previous blood clot
Seek urgent care for a sudden increase in one-sided swelling or pain. Chest pain, unexplained breathlessness, coughing blood, collapse or a very fast heartbeat may indicate pulmonary embolism and require emergency attention.
Prompt review is also important for broken skin, spreading redness, fever or a wound that is not healing.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Vascular Surgery service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
Sudden Leg Pain, Pallor or Coldness: Recognising Acute Limb Ischaemia
Acute limb ischaemia means that blood flow to an arm or leg has suddenly fallen. A clot, embolus or abrupt blockage can deprive tissue of oxygen. Without rapid assessment and treatment, nerves, muscles and the limb itself may be permanently damaged.
This is not the same as gradually developing leg discomfort during walking. Sudden severe symptoms—especially a cold, pale, numb or weak limb—require emergency care.
Key takeaways
- Sudden limb pain with pallor, coldness, numbness or weakness is an emergency.
- Do not massage the limb, apply tight compression or wait for a routine clinic visit.
- Tell emergency staff when symptoms began and whether you use blood thinners.
- Fast treatment aims to restore blood flow and protect tissue.
The six warning signs
Clinicians often describe six Ps: pain, pallor, pulselessness, paraesthesia, paralysis and poikilothermia, meaning unusual coldness. A patient may not have every sign, and a pulse can be difficult to assess without equipment.
Numbness or loss of movement suggests threatened nerves and muscles. These late features make immediate assessment especially important.

Why it can happen
Possible causes include a clot forming in a narrowed artery, a clot travelling from the heart, blockage of a previous bypass or stent, injury, or separation of layers within an artery. Heart-rhythm disorders and established vascular disease can increase risk.
Only urgent examination and imaging can establish the cause. The symptoms should not be self-diagnosed as a cramp or muscle strain.
What to do immediately
Seek emergency medical help. Keep the limb in a neutral, comfortable position and avoid food or drink until medical staff advise, because an urgent procedure may be needed. Bring a medicines list and state the exact time the limb last felt normal.
Do not walk repeatedly to “test” the leg, massage it or use tight bandages. Do not take extra anticoagulant medicine unless instructed by a clinician.
How doctors assess the limb
Assessment may include comparing colour and temperature, checking movement and sensation, feeling pulses and using a handheld Doppler. CT angiography, catheter angiography or other imaging may be required to locate the blockage.
Treatment depends on how threatened the limb is and may involve anticoagulation, clot removal, catheter treatment, angioplasty, stenting or surgery.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Vascular Surgery service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
Vascular Ultrasound Explained: How Doppler Scans Assess Blood Flow
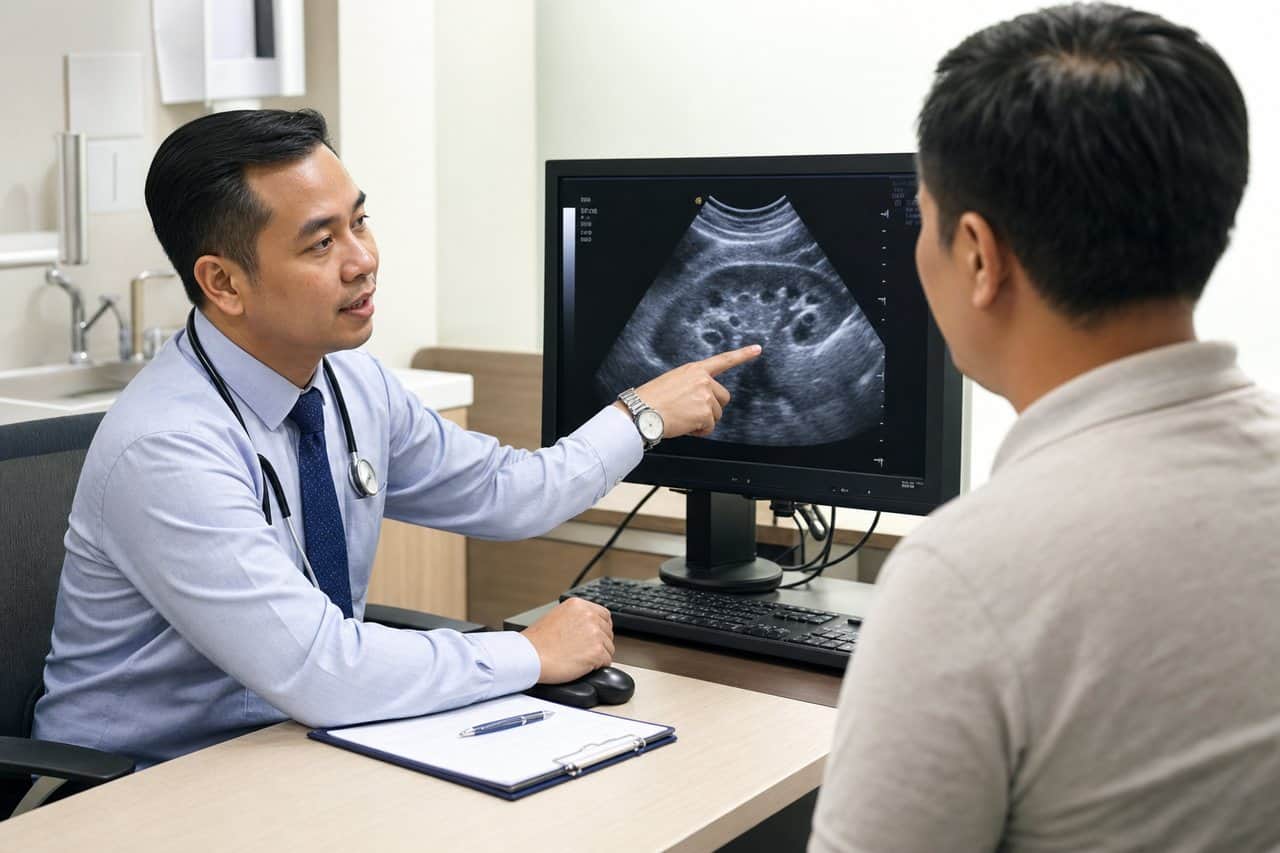
A vascular ultrasound—also called duplex or Doppler ultrasound—uses sound waves to create images of arteries or veins and assess moving blood. It can help identify narrowing, blockage, reflux or a blood clot without ionising radiation.
The scan requested depends on the clinical question. An arterial study, venous clot study and varicose-vein reflux assessment examine different structures and should not be treated as interchangeable tests.
Key takeaways
- Doppler ultrasound evaluates blood direction and speed as well as vessel appearance.
- It may be used for suspected DVT, arterial narrowing, aneurysm or venous reflux.
- Most studies are non-invasive and use gel and a handheld probe.
- A normal scan does not rule out every cause of pain or swelling.
What happens during the scan?
The sonographer exposes the area being examined, applies water-based gel and moves a probe over the skin. You may hear pulsing sounds representing blood flow. Gentle pressure or position changes may be required, especially during a vein study.
The duration varies with the body area and complexity. Some abdominal vascular studies require fasting, while many limb studies do not. Follow the instructions supplied with the appointment.
Questions vascular ultrasound can answer
A venous study can look for deep vein thrombosis. An arterial study can assess reduced blood flow and help locate narrowing. Other protocols evaluate carotid arteries, an enlarged aorta, dialysis access or the direction of flow in varicose veins.
The result must be interpreted alongside symptoms, pulse examination, blood pressure measurements and medical history.
Benefits and limitations
Ultrasound is widely used because it is non-invasive and does not use X-rays. However, deep vessels, heavy calcification, swelling or body habitus can make some areas difficult to assess. Further imaging may be recommended when ultrasound cannot answer the clinical question.
Do not assume that one scan is the best first test for every circulation concern. Clinical assessment determines the correct protocol.
When symptoms should not wait
A suddenly cold, pale, painful or numb limb is an emergency. New one-sided leg swelling with chest pain, breathlessness or coughing blood also requires urgent medical attention. Do not wait for a routine outpatient ultrasound appointment in these situations.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Vascular Surgery service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
High-Fibre Malaysian Foods: How to Increase Fibre Safely
Dietary fibre is found in plant foods such as vegetables, fruit, beans, lentils, whole grains, nuts and seeds. It supports bowel regularity and is associated with long-term health benefits, but suddenly doubling fibre can cause bloating, wind or discomfort.
A safer approach is to increase variety and portions gradually while drinking enough fluid—unless a clinician has prescribed a fluid restriction. Some bowel conditions and recent operations require modified or lower-fibre diets, so general advice is not suitable for everyone.

Key takeaways
- Increase fibre over days or weeks rather than making one large change.
- Use several sources: vegetables, fruit, pulses and whole grains.
- Pair higher fibre with appropriate fluid and regular movement.
- Ask for individual advice if you have bowel narrowing, severe symptoms or recent gastrointestinal surgery.
Malaysian foods that contribute fibre
Useful choices include oats, brown rice, wholemeal bread, dhal, chickpeas, red beans, tempeh, okra, long beans, leafy vegetables, guava, papaya, pear, nuts and seeds. Portion and preparation matter; a food does not need to be imported or expensive to contribute.
Keep edible skins when safe and acceptable, and include vegetables in noodles, soups, curries and mixed dishes. Choose whole fruit more often than strained juice.

A gradual three-step method
First, add one extra vegetable portion to a main meal. Next, replace one refined grain serving with a wholegrain option several times a week. Then add pulses such as dhal or chickpeas in small portions and increase according to tolerance.
If bloating occurs, reduce the latest change and progress more slowly. Different fibre sources affect people differently.
Fluid and movement
Fibre absorbs water. Increasing fibre without suitable fluid can worsen constipation in some people. Sip water across the day and stay physically active within your ability. People with heart failure, kidney disease or another fluid restriction should follow their prescribed allowance.
Persistent constipation may have causes beyond diet, including medicines or medical conditions.

When high fibre may not be appropriate
A temporary low-fibre plan may be used for bowel obstruction risk, certain inflammatory bowel problems, severe diarrhoea or after some operations. Seek assessment for blood in the stool, unexplained weight loss, persistent vomiting, severe abdominal pain or a major change in bowel habit.
A dietitian can help increase fibre without worsening symptoms and can adapt choices for diabetes, kidney disease or food intolerance.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Dietetics service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
Nutrition After Surgery: Protein, Appetite and Wound Healing
Recovery after surgery requires energy, protein, fluids and micronutrients, but appetite may be reduced by pain, nausea, constipation, fatigue or changes in taste. The best plan depends on the operation, medical conditions and instructions from the surgical team.
Nutrition supports healing; it does not replace wound care, movement, medicines or follow-up. Patients who are losing weight or struggling to eat should raise this early rather than waiting until recovery slows.
Key takeaways
- Follow the surgical team’s instructions about when and what you may eat.
- Include a protein source at meals and snacks when medically appropriate.
- Small, frequent meals may be easier when appetite is poor.
- Persistent vomiting, abdominal swelling, dehydration or an infected wound needs medical review.
Why protein matters
Protein supplies amino acids used in tissue repair and maintenance of muscle. Sources may include fish, chicken, eggs, milk, yoghurt, tofu, tempeh, dhal, beans and suitable oral nutrition products. The amount required varies with body size, procedure, kidney function and overall health.
Do not start high-dose protein powders automatically. A dietitian can assess whether ordinary foods are enough and whether a supplement is appropriate.
Work with a small appetite
Try five or six smaller eating opportunities instead of three large plates. Begin with the protein portion, then add carbohydrate and vegetables as tolerated. Enrich meals with milk, yoghurt, egg, tofu or nut paste if these are suitable for you.
Keep easy options available for tired days. Strong cooking smells may worsen nausea, so cooler or simply prepared foods can sometimes be easier.
Fluids, fibre and bowel function
Adequate fluid supports circulation and bowel function, but some heart or kidney patients have fluid restrictions. Follow individual instructions. Constipation may improve with movement, fluids and gradual fibre intake, but certain bowel operations require temporary dietary restrictions.
Do not increase fibre aggressively after gastrointestinal surgery unless the team confirms that it is safe.

When to ask for nutrition support
Seek advice if intake remains very low, weight is falling, swallowing is difficult or you cannot meet recovery needs with ordinary meals. Early nutrition support can be tailored to symptoms and the operation.
Contact the surgical team urgently for repeated vomiting, worsening abdominal pain or swelling, inability to keep fluids down, fever, pus, increasing wound redness or a wound that opens.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Dietetics service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
A Lower-Sodium Malaysian Diet: Reducing Salt Without Losing Flavour
Salt is not only the white crystals added at the table. Sodium can also come from soy sauce, oyster sauce, budu, belacan, stock cubes, processed meats, instant noodles, preserved foods and restaurant gravies. This makes reduction difficult when a meal does not taste obviously salty.
The World Health Organization recommends that adults limit salt to less than 5 grams a day, equivalent to less than 2 grams of sodium. Individual medical advice may differ, particularly for kidney, heart or endocrine conditions.
Key takeaways
- Reduce salty sauces and seasoning gradually so taste preferences have time to adapt.
- Use herbs, spices, citrus, garlic, ginger and aromatics to build flavour.
- Check sodium per serving and the actual number of servings eaten.
- People with kidney disease or medicines affecting potassium should seek individual advice before using salt substitutes.
Where sodium hides in Malaysian meals
A noodle soup may contain sodium in the broth, seasoning powder, fish balls and sauces added at the table. Nasi campur can become high in sodium when several dishes use gravy, sambal, salted fish or preserved ingredients. Bread, crackers and packaged snacks also contribute across the day.
Rather than labelling one cuisine as unhealthy, look at frequency, portion and preparation. The same dish can vary greatly between home cooking and different restaurants.
Practical changes at home
Measure sauces with a teaspoon instead of pouring directly from the bottle. Choose one salty flavouring rather than combining soy sauce, stock powder and table salt. Rinse canned foods when appropriate and compare lower-sodium labels within the same product type.
Add flavour with turmeric, lemongrass, curry leaves, chilli, pepper, lime, onion, garlic and toasted spices. Reduce salt over several weeks; an abrupt change is harder to maintain.
Ordering food outside
Request less sauce or gravy, choose clear portions of vegetables and protein, and avoid drinking all the soup broth. Ask for sauces on the side. Balance a salty meal with less processed choices during the rest of the day instead of skipping meals.
Taste food before adding condiments. A single sachet or spoonful can be more than you need.
Read the label correctly
Compare sodium in products using the same serving size or per 100 grams. Check how many servings are in the packet. Claims such as “reduced sodium” do not mean unlimited use.
A dietitian can adapt lower-sodium advice around appetite, culture, budget, blood pressure, kidney function and other nutritional needs.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Dietetics service. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
Getting a Second Medical Opinion: When It Helps and What to Prepare
A second medical opinion is an independent review of a diagnosis, investigation or treatment recommendation. It can provide reassurance, clarify alternatives or reveal that more information is needed. Seeking another view does not automatically mean that the first doctor was wrong.
The most useful second opinions are focused. Decide what question you want answered and provide complete records so the reviewing clinician can assess the same evidence.

Key takeaways
- Consider another opinion when a diagnosis is uncertain, treatment is major or options carry different trade-offs.
- Bring original reports, imaging, pathology, medicines and a concise clinical timeline.
- Ask the second specialist to explain agreements and disagreements clearly.
- Emergency treatment should not be delayed merely to obtain another routine appointment.
When another opinion may be useful
Patients commonly seek another view before major surgery, long-term treatment or a procedure with significant consequences. It may also help when symptoms continue despite treatment, test findings do not match the clinical picture, or more than one reasonable option exists.
A second opinion is less useful when important records are missing or the question is too broad. Start by writing one or two decisions you need help making.

Build a complete information pack
Prepare clinic letters, discharge summaries, blood results, imaging reports and—where relevant—actual scan images, pathology slides or biopsy reports. Include all current medicines, allergies and previous treatments with dates and outcomes.
Do not selectively remove information because it seems to support one preferred answer. An independent clinician needs the full record to interpret the case responsibly.
How to compare two recommendations
Ask each clinician to explain the working diagnosis, evidence, uncertainty, expected benefit, risks and alternatives. Differences may reflect incomplete data, different clinical experience or more than one acceptable approach.
If opinions differ, ask what additional test or follow-up finding would change the decision. A multidisciplinary discussion may be appropriate for complex conditions.

Do not delay urgent care
Another opinion should not postpone treatment when delay could cause harm. New severe pain, breathing difficulty, sudden weakness, major bleeding or rapid deterioration needs urgent assessment. Tell the second-opinion clinic if there is a time-sensitive recommendation.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Specialist Hospital in Seremban. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
Hospital Consent Forms: Questions to Ask Before a Procedure
Signing a consent form should not be the first time a patient hears the important details of a procedure. Consent is a conversation and decision-making process. The form documents that discussion; it does not replace an explanation that the patient can understand.
Patients can ask questions, request clarification and take reasonable time to consider options unless an emergency makes delay unsafe. Malaysian Medical Council guidance emphasises that valid consent requires capacity, adequate information and a voluntary decision.
Key takeaways
- Understand the purpose, expected benefit, important risks and reasonable alternatives.
- Tell the team about medicines, allergies, pregnancy possibility and previous reactions.
- Ask who will perform the procedure and what recovery or follow-up involves.
- Do not sign until unclear terms or unexpected changes have been explained.
What informed consent should cover
The discussion should explain what is proposed, why it is recommended and what the likely outcome is. Important risks, limitations and reasonable alternatives—including choosing not to proceed—should be discussed in language suitable for the patient.
The amount of detail depends on the procedure and the individual situation. A person with other illnesses, allergies or special risks may need information that is different from another patient having the same procedure.

Questions to ask before signing
Ask: What problem is this procedure intended to address? Are there non-procedure options? What are the common and serious risks? What type of anaesthesia or sedation is planned? How long is recovery likely to take? What restrictions will apply afterwards?
Also confirm whether tissue or samples may be taken, when results are expected, and who to contact if symptoms worsen after discharge.
Medicines and fasting instructions
Provide a complete medicines list, especially anticoagulants, antiplatelet medicines, diabetes treatment and supplements. Never stop these products on your own. The procedural team should give individual instructions.
If fasting is required, confirm the start time and whether clear fluids or morning medicines are allowed. Instructions vary according to the procedure and anaesthetic plan.
Can consent be withdrawn?
A patient can raise new questions or change a decision before the procedure. If the planned procedure changes materially, the clinician should explain why and discuss the updated options whenever circumstances allow.
In genuine emergencies, treatment decisions may need to be made quickly. The healthcare team should still communicate as clearly as the situation permits.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Specialist Hospital. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.
References
Understanding Hospital Referrals: When a Referral Letter May Be Needed
A referral letter is a clinical handover. It tells a specialist why another healthcare professional is requesting an opinion and provides background that may affect assessment or treatment. However, not every private specialist appointment follows exactly the same referral route.
Requirements can depend on the specialty, urgency, insurer, employer panel and hospital policy. Patients should verify the current arrangement directly instead of assuming that a letter is always compulsory—or never needed.
Key takeaways
- Referral rules vary, particularly when insurance or a corporate panel is involved.
- A useful letter includes the reason for referral, relevant history, examination findings, tests and current medicines.
- Urgent symptoms should be directed to emergency care rather than delayed for routine paperwork.
- Keep copies of referral letters and subsequent specialist reports for continuity.
What information does a referral carry?
A referral commonly explains the main concern, how long it has been present, treatment already tried and why specialist input is requested. It may include relevant medical conditions, allergies, pregnancy status, current medicines, laboratory results and imaging.
This background helps the specialist prepare and decide whether additional records or tests are needed. It also reduces the risk that important previous findings are lost between different parts of the health system.
Situations where a letter may matter
Some insurers, managed-care organisations and employer panels require referral documentation or a guarantee letter before they authorise specialist care. Certain specialist services may also prefer a referral so that an appropriate appointment type can be arranged.
Self-paying patients may have different access arrangements. Always ask the hospital and your payer what is required before the visit, because administrative rules can change.
Routine referral or emergency care?
Referral appointments are designed for planned assessment. Severe chest pain, sudden weakness on one side, difficulty breathing, major bleeding, loss of consciousness or a suddenly cold and painful limb should not wait for a routine referral. Seek emergency assistance promptly.
For a concerning but stable problem, tell the referring clinic if symptoms worsen while you are waiting. The clinical team can advise whether the urgency needs to change.
What to do after the specialist visit
Ask how the specialist’s findings will be communicated to the referring clinician. Keep a copy of the clinic letter or report when available. Confirm who will prescribe ongoing medicines, arrange tests and monitor results.
Good referral care is a two-way process: the first clinician provides context, and the specialist returns a focused assessment and plan.
Getting appropriate care in Seremban
For an individual assessment, contact CMH Specialist Hospital. The appropriate specialty, test or urgency depends on your symptoms, medical history and examination.
This article provides general health information and is not a diagnosis or a substitute for personalised medical advice. Seek urgent medical care for severe or rapidly worsening symptoms.