
Inherited Kidney Disease: When Family History Matters

Inherited Kidney Disease: When Family History Matters

A family history of kidney cysts, hearing problems, early kidney failure or unexplained blood in urine can help identify inherited kidney conditions. Here is how patients and families can prepare for an appropriate assessment in Seremban. This guide explains the practical differences patients and families should recognise before seeking care in Seremban.

Inherited diseases include polycystic kidney disease, Alport syndrome and rarer metabolic or structural disorders. Having an affected relative changes risk but does not mean every family member will develop the same severity. Symptoms should be interpreted with the person’s age, medical history, medicines and the way the problem has changed over time. A focused assessment is therefore more useful than judging the condition from a single symptom or online picture.
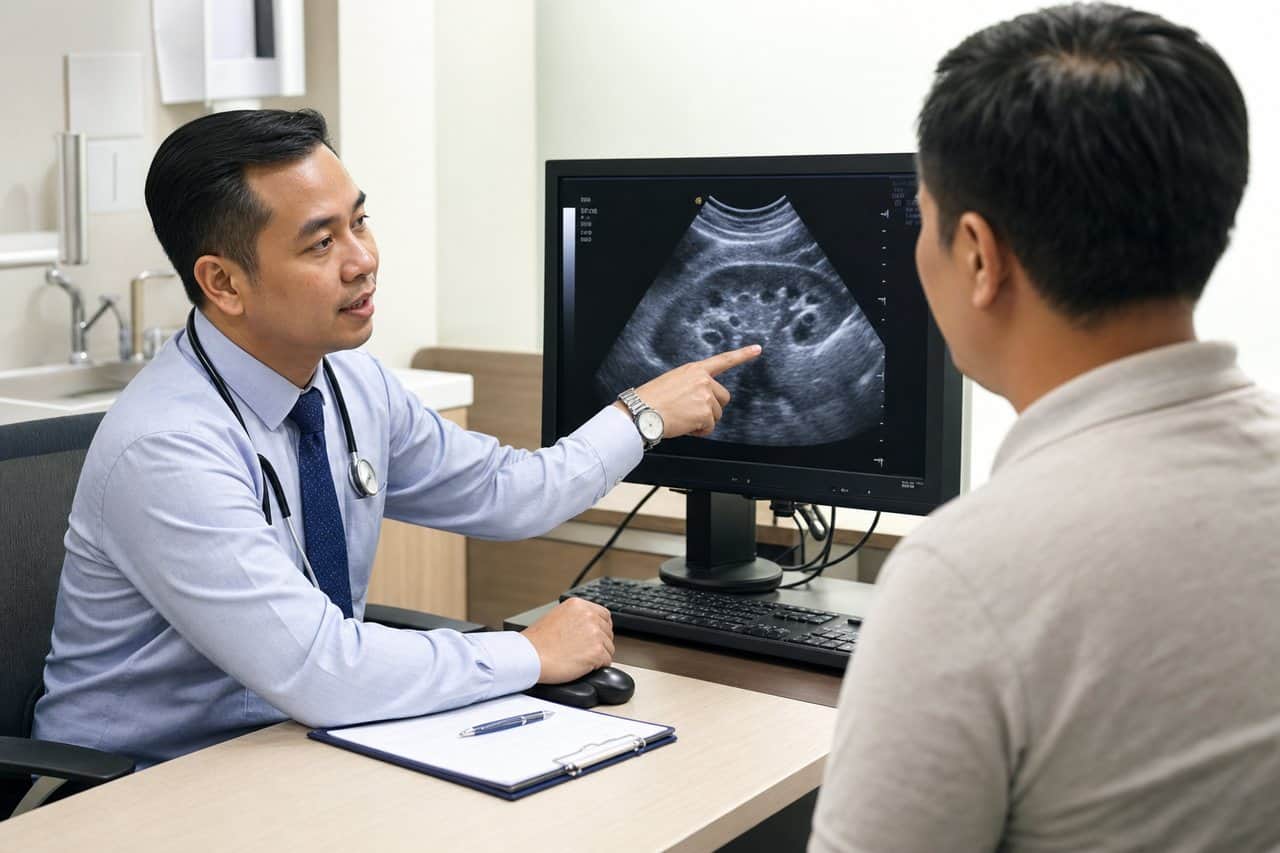
inherited kidney disease family history — kidney ultrasound at CMH
kidney ultrasound at CMH: the first step is matching the symptom pattern with an appropriate clinical assessment.

Key Takeaways

Key pointWhat it means
PatternA family history of kidney cysts, hearing problems, early kidney failure or unexplained blood in urine can help identify inherited kidney conditions.
Possible causesInherited diseases include polycystic kidney disease, Alport syndrome and rarer metabolic or structural disorders.
AssessmentAssessment may include a three-generation family history, blood pressure, urine and kidney-function tests, ultrasound and selective genetic counselling or testing.
TreatmentMonitoring and treatment depend on the specific condition.
Urgent helpPrompt review is needed for visible blood in urine, severe flank pain with fever, very high blood pressure symptoms, sudden reduction in urine or swelling and breathlessness.

Family-history clues that deserve attention

Inherited diseases include polycystic kidney disease, Alport syndrome and rarer metabolic or structural disorders. Having an affected relative changes risk but does not mean every family member will develop the same severity. A short timeline noting frequency, severity and recent changes can make the consultation more useful. The timing, side of the body, triggers, associated symptoms and effect on daily function help separate common explanations from conditions that need earlier review. Guidance from NIDDK: Polycystic kidney disease supports looking at the whole clinical pattern rather than one isolated sign.

inherited kidney disease family history — CMH ultrasound facility
CMH ultrasound facility: investigations are chosen to answer a specific clinical question.

PKD, Alport syndrome and other inherited patterns

Assessment may include a three-generation family history, blood pressure, urine and kidney-function tests, ultrasound and selective genetic counselling or testing. Results can affect both the patient and relatives, so consent and interpretation matter. Prepare allergies, medical conditions and earlier treatment responses so they can be reviewed accurately. A clinician may begin with simple observations and only add tests that can change the diagnosis or next step. NIDDK: What is polycystic kidney disease? provides additional patient guidance about the relevant assessment pathway.

When genetic counselling may be useful

Monitoring and treatment depend on the specific condition. Family screening should follow professional advice because the right age, test and implications differ between disorders. Follow-up is important when the response is incomplete or new symptoms appear. The safest plan also considers other medical conditions, pregnancy where relevant, allergies, kidney or liver function, current medicines and patient preferences. Follow-up should state what improvement is expected and when the plan needs review.

inherited kidney disease family history — kidney results consultation at CMH
kidney results consultation at CMH: follow-up connects test findings with symptoms and response to treatment.

Preparing for an appointment about Inherited kidney disease family history

For inherited kidney disease family history, prepare a brief timeline: the first episode, the most recent episode, frequency, duration and any clear trigger. Note which home measures or prescribed treatments were tried, the dose and the response. Bring relevant reports and images rather than relying on memory. If symptoms come and go, a dated photograph, measurement or symptom diary may help the nephrology team understand what happens between visits.

When Inherited kidney disease family history needs urgent assessment

Prompt review is needed for visible blood in urine, severe flank pain with fever, very high blood pressure symptoms, sudden reduction in urine or swelling and breathlessness. Do not drive yourself when faint, severely breathless or affected by sudden neurological symptoms. These warning signs do not identify one diagnosis, but they can signal that waiting is unsafe. NKF: Kidney disease fact sheet offers further authoritative background; local emergency instructions should take priority when symptoms are acute.

Frequently Asked Questions

Can inherited kidney disease family history improve without specialist treatment?

Some short-lived or mild symptoms improve, but persistence, recurrence or loss of normal function changes the decision. Because inherited kidney disease family history can have more than one cause, an examination is safer than repeatedly trying treatments without a diagnosis.

Does inherited kidney disease family history always require a scan or procedure?

No. Tests are selected after the history and examination. Assessment may include a three-generation family history, blood pressure, urine and kidney-function tests, ultrasound and selective genetic counselling or testing. A scan, laboratory test or procedure is useful only when it is likely to clarify the cause or change management.

What should I record before a nephrology appointment?

For inherited kidney disease family history, write down when the problem started, how often it occurs, what makes it better or worse, and how it affects sleep, work, school or exercise. Bring previous reports, a current medicine list, allergies and relevant family history so that changes can be assessed in context.

Which warning signs make inherited kidney disease family history urgent?

Prompt review is needed for visible blood in urine, severe flank pain with fever, very high blood pressure symptoms, sudden reduction in urine or swelling and breathlessness. When symptoms are severe, rapidly worsening or accompanied by collapse, breathing difficulty or a new neurological problem, use an emergency service rather than waiting for a routine appointment.

Who should assess inherited kidney disease family history in Seremban?

The appropriate starting point for inherited kidney disease family history depends on its pattern and urgency. CMH’s nephrology service can assess problems within this specialty, while emergency symptoms require immediate hospital care. If you are unsure where to start, contact the hospital and describe the main symptom and how quickly it developed.

Getting nephrology care in Seremban

For an individual assessment of inherited kidney disease family history, visit the nephrology service at CMH Specialist Hospital. You can also contact CMH for appointment information. The clinician will decide whether observation, testing, treatment or referral is appropriate after reviewing the full history and examination.

Related CMH Articles

Conclusion

A family history of kidney cysts, hearing problems, early kidney failure or unexplained blood in urine can help identify inherited kidney conditions. The important next step is to match the pace of care to the warning signs and to base treatment on a clinical diagnosis, not on one symptom alone. This article provides general health information and does not replace an examination, diagnosis or personalised advice from a qualified healthcare professional.

References

  1. NIDDK: Polycystic kidney disease
  2. NIDDK: What is polycystic kidney disease?
  3. NKF: Kidney disease fact sheet

Acute Kidney Injury: Causes, Warning Signs and Recovery Monitoring

Acute Kidney Injury: Causes, Warning Signs and Recovery Monitoring

Acute kidney injury means kidney function worsens over hours or days. It can occur during infection, dehydration, urinary blockage or exposure to certain medicines. The sections below outline practical next steps for patients considering specialist care in Seremban. This guide explains the practical differences patients and families should recognise before seeking care in Seremban.

Some patients notice less urine, swelling, nausea, breathlessness or confusion, while others have no obvious symptoms and are diagnosed through blood tests. Older adults and people with chronic disease are at higher risk. Symptoms should be interpreted with the person’s age, medical history, medicines and the way the problem has changed over time. A focused assessment is therefore more useful than judging the condition from a single symptom or online picture.

acute kidney injury Seremban — kidney blood and urine testing at CMH
kidney blood and urine testing at CMH: the first step is matching the symptom pattern with an appropriate clinical assessment.

Key Takeaways

Key pointWhat it means
PatternAcute kidney injury means kidney function worsens over hours or days.
Possible causesSome patients notice less urine, swelling, nausea, breathlessness or confusion, while others have no obvious symptoms and are diagnosed through blood tests.
AssessmentAssessment looks for the cause through examination, medicine review, creatinine and electrolyte tests, urine testing and selective imaging.
TreatmentRecovery varies.
Urgent helpEmergency assessment is needed for little or no urine, severe breathlessness, chest pain, confusion, seizures, persistent vomiting, severe dehydration or rapidly increasing swelling.

How AKI develops over hours or days

Some patients notice less urine, swelling, nausea, breathlessness or confusion, while others have no obvious symptoms and are diagnosed through blood tests. Older adults and people with chronic disease are at higher risk. Record when symptoms begin, their duration, triggers and any effect on sleep or daily activity. The timing, side of the body, triggers, associated symptoms and effect on daily function help separate common explanations from conditions that need earlier review. Guidance from NKF: Acute kidney injury supports looking at the whole clinical pattern rather than one isolated sign.

acute kidney injury Seremban — CMH nephrology service
CMH nephrology service: investigations are chosen to answer a specific clinical question.

Blood, urine and imaging tests for the cause

Assessment looks for the cause through examination, medicine review, creatinine and electrolyte tests, urine testing and selective imaging. Treatment may involve fluids, infection care, relieving obstruction or temporarily changing contributing medicines. Previous test results and the names and doses of current medicines provide important context. A clinician may begin with simple observations and only add tests that can change the diagnosis or next step. NKF: Acute kidney injury patient guide provides additional patient guidance about the relevant assessment pathway.

Recovery does not end when creatinine improves

Recovery varies. Follow-up kidney and urine tests are important because an episode raises the risk of future acute injury and chronic kidney disease even when the person feels better. Confirm which changes are expected, which are not, and who to contact if symptoms worsen. The safest plan also considers other medical conditions, pregnancy where relevant, allergies, kidney or liver function, current medicines and patient preferences. Follow-up should state what improvement is expected and when the plan needs review.

acute kidney injury Seremban — CMH Laboratory
CMH Laboratory: follow-up connects test findings with symptoms and response to treatment.

Preparing for an appointment about Acute kidney injury

For acute kidney injury, prepare a brief timeline: the first episode, the most recent episode, frequency, duration and any clear trigger. Note which home measures or prescribed treatments were tried, the dose and the response. Bring relevant reports and images rather than relying on memory. If symptoms come and go, a dated photograph, measurement or symptom diary may help the nephrology team understand what happens between visits.

When Acute kidney injury needs urgent assessment

Emergency assessment is needed for little or no urine, severe breathlessness, chest pain, confusion, seizures, persistent vomiting, severe dehydration or rapidly increasing swelling. Emergency symptoms require immediate attention even if a routine specialist visit is already arranged. These warning signs do not identify one diagnosis, but they can signal that waiting is unsafe. NKF: Understanding kidney function tests offers further authoritative background; local emergency instructions should take priority when symptoms are acute.

Frequently Asked Questions

Can acute kidney injury improve without specialist treatment?

Some short-lived or mild symptoms improve, but persistence, recurrence or loss of normal function changes the decision. Because acute kidney injury can have more than one cause, an examination is safer than repeatedly trying treatments without a diagnosis.

Does acute kidney injury always require a scan or procedure?

No. Tests are selected after the history and examination. Assessment looks for the cause through examination, medicine review, creatinine and electrolyte tests, urine testing and selective imaging. A scan, laboratory test or procedure is useful only when it is likely to clarify the cause or change management.

What should I record before a nephrology appointment?

For acute kidney injury, write down when the problem started, how often it occurs, what makes it better or worse, and how it affects sleep, work, school or exercise. Bring previous reports, a current medicine list, allergies and relevant family history so that changes can be assessed in context.

Which warning signs make acute kidney injury urgent?

Emergency assessment is needed for little or no urine, severe breathlessness, chest pain, confusion, seizures, persistent vomiting, severe dehydration or rapidly increasing swelling. When symptoms are severe, rapidly worsening or accompanied by collapse, breathing difficulty or a new neurological problem, use an emergency service rather than waiting for a routine appointment.

Who should assess acute kidney injury in Seremban?

The appropriate starting point for acute kidney injury depends on its pattern and urgency. CMH’s nephrology service can assess problems within this specialty, while emergency symptoms require immediate hospital care. If you are unsure where to start, contact the hospital and describe the main symptom and how quickly it developed.

Getting nephrology care in Seremban

For an individual assessment of acute kidney injury, visit the nephrology service at CMH Specialist Hospital. You can also contact CMH for appointment information. The clinician will decide whether observation, testing, treatment or referral is appropriate after reviewing the full history and examination.

Related CMH Articles

Conclusion

Acute kidney injury means kidney function worsens over hours or days. The important next step is to match the pace of care to the warning signs and to base treatment on a clinical diagnosis, not on one symptom alone. This article provides general health information and does not replace an examination, diagnosis or personalised advice from a qualified healthcare professional.

References

  1. NKF: Acute kidney injury
  2. NKF: Acute kidney injury patient guide
  3. NKF: Understanding kidney function tests